


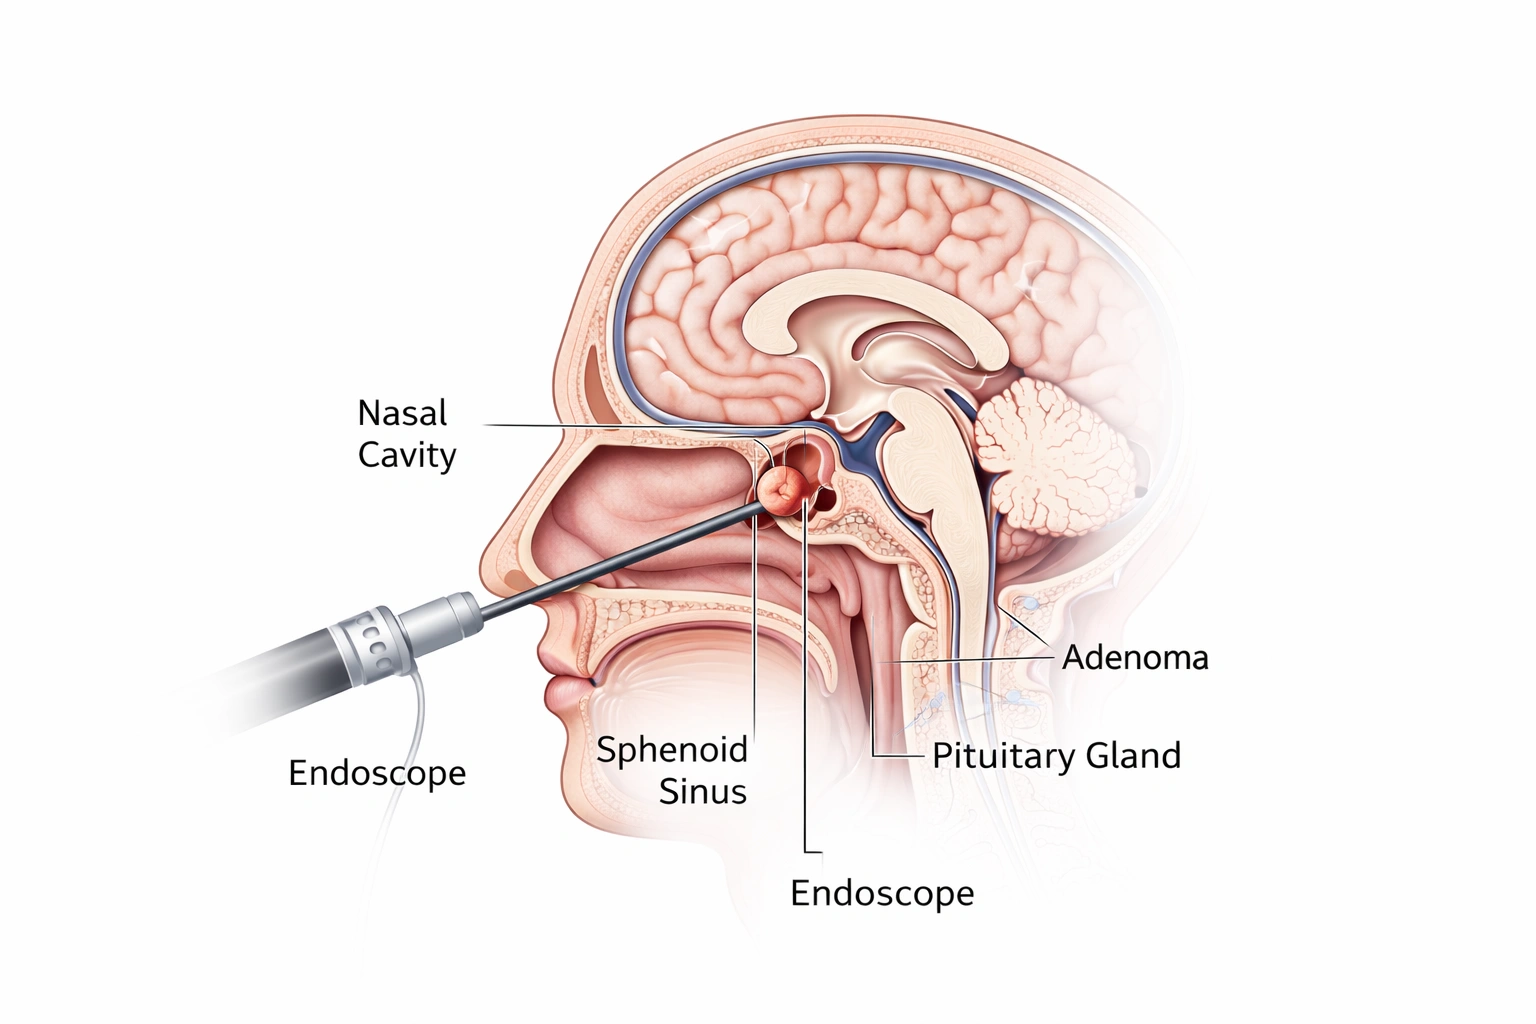
Pituitary adenoma surgery is the removal of masses in the pituitary gland, the “central hormone control centre” located at the base of the brain.
In current surgical practice, this procedure is performed through the nostrils, a natural opening, without opening the skull.
Known in the medical literature as “Endoscopic Transsphenoidal Surgery”, this method is the most advanced technique for reaching the tumour without touching the brain tissue.
What Is a Pituitary Adenoma and Why Is Surgery Needed?
A pituitary tumour (pituitary adenoma) is a mass that originates from the pituitary gland. It is usually benign, but it can cause serious clinical problems through hormonal imbalance and pressure on the optic nerves.
These masses require surgery for two main reasons: hormonal imbalance and mass effect.
Adenomas that secrete excess hormones (functional adenomas) can lead to serious systemic diseases such as acromegaly, Cushing’s disease or prolactinoma.
Adenomas that do not secrete hormones but keep growing press on the optic nerves just above them (optic chiasm) and cause visual field loss.
From the perspective of functional neurosurgery, this makes it essential to carry out preoperative visual field tests and endocrine work-up alongside the surgical decision.
What Is the Nasal (Transsphenoidal) Approach in Pituitary Adenoma Surgery?
In the transsphenoidal approach, the surgeon passes through the nasal cavity to reach an air space called the sphenoid sinus, and from there enters the “sella turcica” (Turkish saddle), where the pituitary gland sits.
High-resolution endoscopes are used in this method. The endoscope lets the surgeon see the tumour from very close range, at a wide angle and under bright light.
Why Is Pituitary Surgery Performed Through the Nose?
The pituitary gland lies directly behind the nasal cavity, at the lowest part of the brain. This strategic location turns the nasal passage into a natural corridor.
Direct Access Without Harming Brain Tissue
In conventional operations performed from the top or side of the skull (craniotomy), the surgeon has to retract or lift brain tissue to reach the pituitary gland.
In surgery through the nose, there is no contact with brain tissue. Because the approach proceeds directly from the skull base, the delicate lobes of the brain stay outside the operating field.
This approach reflects the core principle of endoscopic skull base surgery: reaching the tumour through the body’s natural openings without touching the brain.
Treatment Without Opening the Skull (No Craniotomy)
Traditional brain operations involve large incisions in the scalp and a bone window cut into the skull.
Surgery through the nose leaves no visible incision. This is a major advantage in terms of preserving the body’s integrity.
Prof. Dr. Erdinç Özek: The aim of pituitary surgery is not only to remove the tumour. The main reason for choosing the nasal route is to protect the healthy parts of the pituitary gland and the surrounding vital blood vessels and nerves with the greatest possible precision. This surgery is a high-technology discipline performed within a space measured in millimetres.
Advantages of Endoscopic Pituitary Surgery Through the Nose
Because the endoscopic technique offers a wider field of view and greater manoeuvrability than the microscopic method, it brings many advantages.
Cosmetic Advantages: No Stitches, No Scars
Since the operation is performed entirely through the nose, no scar is left on the face or scalp.
After surgery, nothing in the patient’s appearance shows that they have had an operation.
Short Recovery and Early Discharge
- Because the brain tissue is not handled and the skull is not opened, recovery is very fast.
- Patients can usually be discharged on the 2nd or 3rd day after surgery.
- Patients return to social and working life weeks earlier than after conventional surgery.
Protecting and Restoring Vision
- The tumour presses on the optic nerves from below.
- Surgery through the nose also approaches the tumour from below.
- As a result, the pressure on the nerves can be relieved safely without risking damage to them.
- Many patients notice an improvement in their vision soon after surgery.
In patients with vision loss, the speed and extent of postoperative recovery can be predicted in advance with preoperative visual field tests performed as part of brain and spinal cord tumour surgery.
Minimising the Risk of Complications
The risks of brain haemorrhage, infection and neurological damage are markedly lower than with craniotomy.
In particular, the image quality provided by the endoscope makes it easier to distinguish the tumour from healthy tissue.
| Feature | Nasal Route (Endoscopic) | Conventional Route (Craniotomy) |
| Incision | Inside the nose (invisible) | Scalp and skull |
| Brain retraction | None | Required |
| Hospital stay | 2–3 days | 5–10 days |
| Recovery time | 1–2 weeks | 4–8 weeks |
| Visualisation | Wide-angle endoscope | Microscope |
The Procedure: How Is a Pituitary Tumour Reached Through the Nose?
- The process begins with preparing advanced surgical navigation systems and endoscopic equipment.
- The surgeon enters through the nostrils and creates a pathway through the mucosa.
- The air space behind the nasal cavity (sphenoid sinus) is reached and its back wall is crossed.
- The bone of the sella turcica is opened to expose the pituitary gland and the tumour. The tumour is removed piece by piece with special micro-instruments.
- At the end of the operation, the area is sometimes sealed with the patient’s own tissue (fat or membrane) to prevent cerebrospinal fluid (CSF) leakage.
Who Is Suitable for Pituitary Surgery Through the Nose?
- More than 95% of pituitary adenomas can be operated on with this method.
- Microadenomas: hormone-secreting masses smaller than 1 cm.
- Macroadenomas: masses larger than 1 cm that press on the optic nerve.
- Recurrent cases: it can also be used in patients who have had previous surgery.
However, in very rare cases where the tumour is very extensive or the nasal anatomy does not allow surgery, a different approach may be needed.
Recovery After Surgery and What to Watch For
Recovery is usually comfortable, but a few critical rules must be followed.
- Fluid Balance: In the first days after surgery, urine output and fluid intake are closely monitored (because of the risk of diabetes insipidus).
- Avoiding Pressure: Heavy lifting, blowing the nose and straining are not allowed for the first few weeks. This protects the healing membranes around the brain.
- Hormone Monitoring: Blood tests are performed to make sure the pituitary gland is functioning fully.
During postoperative hormonal follow-up, working together with an endocrinologist, combined with neuro-oncology monitoring, allows the tumour’s biological behaviour to be tracked over the long term.
Prof. Dr. Erdinç Özek: A slight feeling of fullness in the nose after surgery is normal. However, if clear, watery fluid comes from the nose, see a doctor immediately. This may be a sign that cerebrospinal fluid is leaking from the sealed area, and it needs prompt treatment.
This information is for general guidance only; please consult a healthcare provider about your own condition.
Frequently Asked Questions
Does pituitary surgery change the shape of the nose?
Because the endoscopic method is performed entirely through the nostrils, there is no external incision and the nasal bone is not altered. As a result, there is no cosmetic change or deformity in the outer appearance of the nose after surgery.
What is the risk of brain damage during surgery?
In surgery through the nose, brain retraction (pulling the brain aside) is not performed. Because the surgeon reaches the tumour directly from the skull base, the risk of damage to brain tissue is much lower than in conventional open surgery.
How long does surgery through the nose take?
The length of the operation depends on the size of the tumour, its relationship with surrounding tissue and whether the patient has had previous surgery. In general, endoscopic pituitary surgery takes between 1.5 and 3 hours.
Is nasal packing used after surgery?
Modern endoscopic techniques generally avoid the traditional large gauze packs that block breathing. In most cases, special materials are used that keep the patient comfortable, dissolve on their own or allow breathing.
Can a pituitary tumour come back after surgery?
When the tumour is completely removed, the recurrence rate is quite low, although the type of adenoma and its spread into surrounding tissue affect this. Regular follow-up with hormone tests and MRI scans after surgery is essential for managing this risk.
Scientific References
Endoscopic Endonasal Pituitary Surgery – Mayo Clinic Proceedings
Endoscopic vs Microscopic Transsphenoidal Surgery – PubMed/NIH
Pituitary Adenoma Management Guidelines – European Journal of Endocrinology
